-

IMPLEMENTATION OF THE CEASE BUNDLE IN THE PEDIATRIC ICU
Ayanna Brown-Gomez
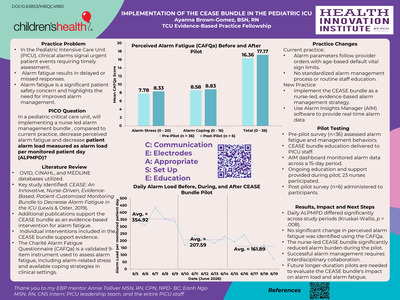
Practice Problem: Clinical alarms in the Pediatric Intensive Care Unit (PICU) are intended to indicate potentially life-threatening events requiring timely assessment. Excessive alarm frequency can contribute to alarm fatigue, resulting in delayed or missed responses and creating a significant patient safety concern that must be assessed in a timely manner. There is a need to address alarm management. [AT1.1] Literature Review: A literature search was conducted using OVID, Medline, and CINAHL. A quasi-experimental research study demonstrated the CEASE bundle as an effective nurse-led alarm management strategy. Multiple systematic reviews support several interventions included within the bundle. The literature review also identified the Charite Alarm Fatigue Questionnaire (CAFQa) as a validated 9-item instrument for measuring alarm fatigue, including alarm-related stress and coping behaviors in clinical settings.[AT2.1] Practice Change: Prior to implementation, the PICU lacked a standardized alarm management practice. Alarm parameters were based on age-specific default settings and were not consistently individualized to patient condition. The CEASE bundle, consisting of Communication, Electrodes, Appropriateness, Setup, and Education, was implemented to reduce nonactionable alarms through a structured, nurse-led approach. Implementation/Pilot Testing: A 5-Day CEASE bundle pilot was conducted in the PICU. A pre-pilot survey assessed alarm fatigue and alarm management behaviors among PICU nurses. Staff received CEASE bundle education through staff and unit-based council meetings. Alarm data was collected before, during, and after implementation using the Alarm Insights Manager (AIM) dashboard. A post-pilot survey was completed by participating nurses. Results: A Kruskal-Wallis test demonstrated a statistically significant decrease in daily alarm load across pilot periods (p=0.008). No statistically significant change was observed in perceived alarm fatigue as measured by the CAFQa. Recommendations/Conclusion: Implementation of the CEASE bundle significantly reduced alarm burden in the PICU. Future studies with longer implementation periods are recommended to evaluate the sustainability of alarm reduction and its impact on perceived alarm fatigue. [
-

Implementing the Community Health Worker Role Into a Nurse-Led Diabetes Management Program
Blanca Cruz Escalante
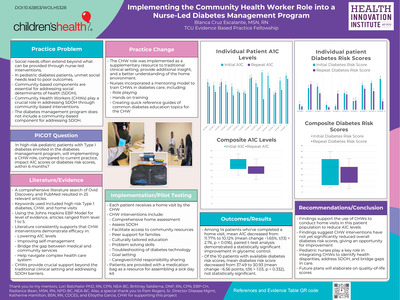
Practice Problem: Unmet social needs lead to poor outcomes in pediatric diabetes patients. While nurse-led interventions such as follow-up calls and care coordination can improve self-management of diabetes, social needs often extend beyond what nurses can directly provide. At the project facility, the diabetes management program historically has not included a community-based component, essential for addressing social determinants of health (SDOH). Notably, Community Health Workers (CHWs) play a crucial role in addressing health disparities through community-based interventions. To examine this practice gap, the following PICOT question was developed: In high-risk pediatric patients with Type 1 diabetes (T1D) enrolled in the diabetes management program, will implementing a CHW role, compared to current practice, impact A1C levels or diabetes risk scores, within 6 months?
Literature/Evidence: A comprehensive literature search of Ovid Discovery and PubMed resulted in 25 relevant articles, including randomized control trials and systemic reviews. The keywords used included high risk T1D, home visits, and CHW. Using the Johns Hopkins EBP Model for levels of evidence, the articles ranged from level 1 to 5. The literature consistently supports that CHW interventions demonstrate efficacy in lowering A1C and improving self-management. In addition, CHWs bridge the gap between medical and community services, while helping to navigate the complex health care system. CHWs provide crucial support beyond the traditional clinical setting and play a key role in addressing SDOH barriers that can adversely affect diabetes care in children.
Practice Change(s): The CHW role was implemented as a supplementary resource to traditional clinical setting, conduct home visits, provide additional insight, and a better understanding of the home environment. Nurses incorporated a mentoring model to train CHWs in diabetes care, including role playing and hands on training.
Implementation/Pilot Testing: A home visit is completed for each patient. CHW interventions include a comprehensive home assessment, assessment of SDOH, facilitating access to community resources, and providing peer support to families. In addition, CHWs offer culturally tailored education, problem solving and troubleshooting of diabetes technology, goal setting, and caregiver/child responsibility sharing. Patients are provided with a medication bag as a resource for assembling a sick day kit.
Outcomes/Results: Among 14 patients who have completed a home visit, mean A1C decreased from 11.77% to 10.12% (mean change −1.65%, t(13) = 2.76, p = 0.016), paired t-test analysis demonstrated a statistically significant improvement in glycemic control. Among 10 patients with available diabetes risk scores, the mean scores decreased from 37.49 to 30.93 (mean change −6.56 points, t(9) = 1.03, p = 0.332). While not statistically significant, the reduction suggests a clinically significant trend supporting the intervention.
Recommendations/Conclusions: Findings support the use of CHWs to conduct home visits in this patient population to reduce A1C levels. CHW interventions have not yet significantly reduced overall diabetes risk scores, which gives an opportunity for improvement. Limitations include small sample size and short time frame given project remains in pilot phase. Indeed, pediatric nurses play a key role in integrating CHWs to identify health disparities, address SDOH, and bridge gaps in care. Future plans will elaborate on quality-of-life scores. -

AID Me! Introducing Health Literate Insulin Pump Training Materials into Patient
Katherine Hamilton Doyle
Practice Problem: Automated Insulin Delivery (AID) systems are insulin pumps that communicate with continuous glucose monitors to administer insulin at set intervals to alter one’s blood glucose to a preset target. AID systems have been proven to lower patients’ Hemoglobin A1Cs, but successful operation of the AID system can be complicated for patients and their families. This can lead to diabetes-related emergency room visits and hospital admissions. In a review of 164 patients started on an AID system over a period of six months, 27 patients visited the emergency department for a diabetes-related reason and 18 of those patients were admitted. To address this issue, an evidence-based practice project was designed using the PICOT question: In children diagnosed with diabetes mellitus (P), what is the effect of introducing health literate educational materials (I) compared to current practice (C) on diabetes related admissions and emergency department visits (O) within three months of automated insulin delivery system initiation (T).
Literature/Evidence: A literature search utilizing EBSCO and OVID yielded twenty-three peer reviewed articles ranging from level I to level V of evidence. Key words for the search included diabetes mellitus, diabetic ketoacidosis, automated insulin delivery, insulin pumps, adverse events, patient education, cost and health literacy. Key findings include the importance of health literate education for proper self-management, the importance of ketone management teaching, and the importance of avoiding DKA readmissions for long term patient health outcomes as well as for cost reduction to the healthcare system.
Practice Change(s): The practice change in this evidence-based practice project involved editing tip sheets provided in the insulin pump initiation training to be more health literate. The Flesch-Kincaid system rates readability from 0 (difficult to read) to 100 (very easy to read). Prior to the change, the patient education materials had a 41.5 Flesch Reading Ease score and were scored on the Flesch-Kincaid Grade Level at 10.0. These tip sheets will replace the current tip sheets handed out in an insulin pump initiation class.
Implementation/Pilot Testing: Pilot testing of the new health literate patient educational materials began on 7/20/2026. Handouts were distributed to diabetes educators who will place the handouts in patient folders to take home from class. It is expected that preliminary results will be available on 11/20/2026. Outcomes/Results: The health literate patient education materials have a Flesch Reading Ease Score of 78.4 and a Flesch-Kincaid Grade Level of 4.9. This shows an improvement of 36.9 in the reading ease score and five grade levels. I expect a decrease in hospitalizations and/or emergency department utilization at the tips sheets now provide easily understood instructions for the prevention of ketosis due to pump malfunction.
Recommendations/Conclusions: There is robust evidence to support making diabetes education materials health literate, especially information regarding ketone prevention and insulin pump management. Patients should receive consistent information and will need continued education support with their diabetes self-management throughout their lifetime. Clinicians should design tools that are easy for patients to understand. -

Moving to Adult Care: The Impact of Transition Readiness Assessments in the HCT of YAs with Epilepsy
Tanika A. Middleton and shley McCool
Practice Problem: Health Care Transition (HCT), the process of planning, preparing, transferring from pediatric healthcare and integrating into adult healthcare, is increasingly necessary as more adolescents with complex and chronic health conditions reach adulthood. Assessing transition readiness is identified as a key component of HCT. At a large, academic pediatric healthcare system, there was an opportunity to more consistently incorporate readiness assessments in HCT services of specialty clinics and determine the impact of readiness assessments on HCT outcomes. To address this, an evidence-based practice project was implemented using the following PICOT question: In patients ages 18-22 seen in the outpatient Epilepsy Clinic, does implementation of a structured transition readiness assessment increase the number of successful transfers to adult care? Successful transfer was defined as having a scheduled appointment in adult care. Literature/Evidence: Using OVID Synthesis and PubMed, a comprehensive literature review of 14 articles was conducted to explore use, role, and outcomes of transition readiness assessments in epilepsy and other pediatric patient populations. Across literature, evidence supported implementation of the Transition Readiness Assessment Questionnaire (TRAQ). TRAQ is the third iteration of a validated tool used internationally to assess adolescent and young adult HCT readiness using 20 questions, 4 domains, plus 2 questions on confidence and importance in managing health care. Practice Change(s): To identify and understand the impact of readiness assessments on HCT success, a practice change was implemented to begin administering TRAQ 5.0 to assess HCT readiness of young adult patients. This tool was available for use within the pediatric healthcare system. This practice change was adopted by clinic leadership and the interdisciplinary care team as the next phase of a long-term strategy to implement HCT services through cycles of improvement. Implementation/Pilot Testing: A 16-week pilot in the outpatient epilepsy clinic started in March 2026. Established patient ages 18-22 with an epilepsy diagnosis and a scheduled in-person follow-up visit with a provider were assigned TRAQ, in English or Spanish, to complete in the electronic medical record (EMR) patient portal within 7 days of the visit. If TRAQ was not completed prior to the visit, patients or parents/caregivers were directed to complete TRAQ at check-in using a tablet. Providers were able to view TRAQ results in the EMR. Weekly reports were utilized to track and monitor pilot progress. Updates were shared during monthly interdisciplinary care team meetings. Upon completion of the pilot, data was reviewed and analyzed to evaluate outcomes. Outcomes/Results:133 patients met inclusion criteria. 72 TRAQs were completed, with a 78% completion rate. Five referrals to adult care were made and four referrals resulted in scheduled or completed visits in adult care. Recommendations/Conclusions: Continued evaluation of the impact of readiness assessments on HCT is needed for patients with epilepsy and expanding to other complex and chronic diagnoses are future directions of this work. Other factors such as coordination of care and improvements in referral processes may also be contributing to successful HCT. Strategic alignment, physician and operational leadership support, and interdisciplinary collaboration are key drivers of successful implementation of practice changes targeting HCT services and interventions.
-

Engaging the Nurse’s Voice: Committee Alignment in the Unit Practice Council
Kris Noel
Practice Problem: In this multi-site hospital system, unit committees were meeting outside of the Unit Practice Council (UPC) but were not consistently returning to the council to share information, request input, or seek decisions. This created a disconnect between committee work and nursing priorities. To address this problem, an evidence-based practice project was initiated using the PICO(T) question: Does the practice of having all unit committees report to their Unit Practice Council (UPC) to share information and for decision-making improve nurse engagement compared to the current practice of multiple committees meeting outside of their UPC within a three-month pilot period? Literature/Evidence: A comprehensive literature search used Library Services and OVID synthesis to search CINAHL and PubMed databases with the key terms: nursing professional governance, unit practice council, shared governance, unit-based council and engagement. Nursing Professional Governance (NPG) literature supports the UPC as the unit's decision-making body for nursing practice, quality, competence, and knowledge. Evidence also supports strengthening communication, frontline nurse participation, and accountability for unit-based practice changes through governance structures. Best practice indicates that committees should inform the UPC, bring forward concerns, seek input from council members, and return for decisions that fall within their authority. Practice Change(s): After gaining approval from unit leadership, the Cardiac Intensive Care Unit (CICU) was selected as the focus of this work due to its overall size, established UPC, and existing committee structure. A pilot was implemented to align unit committees through the UPC. During monthly UPC meetings, each committee utilized a template to provide a 90-second report. These reports included the top three strengths and weaknesses identified during the previous month, requests for input from UPC members, and discussion of issues requiring council feedback or decisions requiring approval. Implementation/Pilot Testing: Zoom training for the pilot was provided to the managers, UPC leaders, and the chairs of the four committees operating outside the UPC. A script was provided for the chairs. A survey was created to measure nurse engagement. Pre-intervention surveys (n=156) yielded a response rate of approximately 19%. The pilot ran for three months, with committee representatives providing monthly UPC updates using the standardized reporting format. The post-intervention response rate was 9%. Outcomes/Results: An independent-samples t-test was conducted to compare pre- and post-survey responses. Nurse engagement scores improved following the intervention, with statistically significant increases in nurses' perceived involvement in nursing practice decisions and willingness to submit practice-improvement ideas to the UPC. Perceptions that the UPC made decisions that positively impacted practice improved. The results showed that nurses who participated in NPG activities had significantly higher overall engagement scores. Significant improvements were observed in understanding the role of the UPC, willingness to propose practice-improvement ideas, and accountability for nursing practice. Recommendations/Conclusions: Aligning committees through the UPC improved communication, increased visibility of committee work and strengthened nurse engagement in the CICU. This project supports the UPC as the decision-making body for nursing practice. Continued intentional committee alignment with UPCs and greater communication with all nurses are crucial for increasing engagement in decision-making and enculturating NPG throughout the organization.
-

Pulse (Ox) Check! Smarter Monitoring, Stronger Outcomes
Christina Reyna
Practice Problem: Infants and children are a vulnerable patient population at an inherently higher risk of detrimental effects of hypoxia or hypoxemia. Literature shows that early detection of hypoxemia can facilitate timely interventions which in turn can reduce morbidity and mortality. On an inpatient pediatric pulmonary unit, there have been multiple instances of staff concern for inaccurate pulse oximetry readings, leading to evaluation of potential technological interventions to improve early detection of hypoxia. In one year, there were 3 code/MET events, in which uncertainty of device accuracy delayed response time and interventions. To address this problem, an evidence-based practice project was implemented using the PICOT question: In respiratory technology dependent pediatric patients (P), how does alternative oximetry monitoring (I) compared to current oximetry monitoring (C) affect early notification of decreased oxygen saturation (O)? A different type of pulse oximetry device was evaluated to determine if pulsatile signal tracking technology would improve early detection of decreased oxygen saturation. Detection of low oxygen saturation earlier allows for quicker interventions, improving overall patient safety and outcomes. Literature/Evidence: A comprehensive literature search using Children’s Health Library, Medline, and Scopus databases was conducted using key terms including pulse oximetry, pediatric, hypoxia, arterial, and accuracy. The search yielded 24 articles including systematic reviews and randomized controlled trial. Literature suggests that overestimation of oxygen saturation by pulse oximeters, particularly in hypoxic states, is higher in darker pigmented skin tone or states of lower perfusion. Readings may also be influenced by factors such as the method of oxygen saturation measurement (e.g., venous versus capillary). On the inpatient pediatric pulmonary unit, 76% of the patient population during 2025–2026 is Hispanic or African American which correlates with darker pigmented skin, making this an important consideration when interpreting pulse oximetry measurements. Practice Change(s): The practice change was focused on an inpatient technology dependent pulmonary unit staffed with both core nursing and respiratory therapists. Prior to pilot, meetings with organization value analysis representatives, nursing leadership, vendors for pulse oximetry, and physiological monitor representatives determined how best to compare current pulse oximeter to trialed pulse oximeter. Key stakeholders and nursing leaders supported pilot. Both the existing pulse ox and piloted pulse ox remained in place for the duration of pilot to ensure appropriate monitoring and connection to electronic medical record documentation. Implementation/Pilot Testing: A total of ten patients were included in pilot with side-by-side comparison of both products over a five-day period. Inclusion patients had darker pigmented skin, and baseline lower perfusion with a variety of complex pulmonary diagnosis, including bronchomalacia, pulmonary hypertension, restrictive lung disease, obstructive sleep apnea, and bronchiolitis. The respiratory support for patients ranged from non-invasive bi-level positive pressure and continuous positive pressure ventilation, tracheostomy and ventilator dependent, heated trach collar, and heated high flow nasal cannula. Outcomes/Results: Side by side comparison included recording minute by minute oxygen saturation and heart rate from both devices. Both nurses and respiratory therapists were surveyed during pilot with 45 total responses. Respondents had 89% confidence that piloted pulse oximeter correlated with other clinical signs/symptoms, 60% had confidence of piloted pulse oximeter accuracy, with an overall 53% product preference. The bedside staff recorded and/or time stamped desaturation event details, that allowed review of minute-by-minute data. These results indicated that the piloted pulse oximeter picked up desaturations and responded to clinical interventions quicker than current pulse oximeter. In addition, the heart rate detected by the piloted pulse oximeter correlated consistently with heart rate detected by electrocardiogram (ECG) leads and two occasions with exact correlation to blood gas O2 saturation value. Recommendations/Conclusions: While this pilot was limited by its small sample size and short duration, the results support expansion of pilot to gather data in critical care settings. Next steps include expanded pilot and evaluation of piloted pulse oximeter for system use.
-

Use of Standard Visual Education Tools to Improve NPO Compliance in Pediatric Day Surgery
Alma Rivera
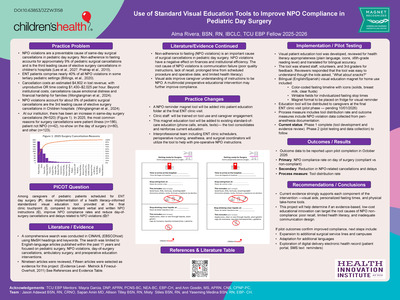
Practice Problem Non-compliance with perioperative fasting (NPO) instructions is an ongoing safety and operational challenge in pediatric day surgery. Day-of-surgery cancellations result in financial losses, with unproductive OR time costing $1,430-$2,025 per hour. NPO violations cause 4.5% - 13.6% of lost OR time in children's hospitals and are the third leading cause of elective surgery cancellations. At our pediatric hospital, NPO violations contribute to same-day surgical delays and cancellations, particularly in the high-volume Otolaryngology (ENT) service line. This Evidence-Based Practice (EBP) project sought to answer whether, among caregivers of pediatric patients scheduled for ENT Day surgery (P), implementing a health literacy-informed standardized visual education tool at the final touchpoint (I), compared with standard verbal and written NPO instructions (C), improves NPO compliance rates and reduces day-of-surgery cancellations and delays related to NPO violations (O)? Literature/Evidence A medical librarian assisted with a literature search, resulting in 19 papers appraised with AACN Levels of Evidence, with 16 included in this EBP Project. Databases searched were PubMed, CINAHL, and Cochrane Library, using terms like pediatric NPO compliance, preoperative fasting education, visual education tools, surgical cancellations for children, and health literacy perioperatively. Inclusion criteria: pediatric populations, published 2014-2024, in English. Articles with evidence levels III to V were reviewed. Literature indicates that patients or caregivers forget 40-80% of medical information immediately after consultation, with about half of this information being incorrect. Visual aids nearly double caregivers' ability to identify fasting reasons. Personalized instruction tools at home reinforce recall and enable review. Providing pre-calculated fasting stop times reduces caregiver confusion and unnecessary fasting. Practice Change An interprofessional team was engaged and included ENT clinic schedulers, perioperative staff, anesthesia providers, and surgical coordinators. A bilingual, health literacy-informed visual education tool was developed and added to the patient folder and given before surgery. The tool included visual fasting guidelines, writable fields for stop times, and a pre-surgery checklist. Staff received brief training to explain its use and promote caregiver engagement. Implementation/Pilot-Testing During planning and pilot testing, the visual tool was developed and reviewed for health literacy and bilingual accuracy. Future pilot testing would include providing the tool to caregivers at the final ENT visit. Existing standard of care education steps, like pre-op phone calls and electronic messages with NPO times, will remain unchanged. A process measure tracking tool will monitor patient distribution rates, with outcome data from routine peri-anesthesia documentation on surgery day using de-identified, aggregate data. Outcomes/Results The primary outcome would be measured by NPO compliance rates on the day of surgery, documented in preoperative assessments. Secondary outcomes include fewer NPO-related cancellations and delays. Process measures, like tool distribution among ENT Day surgery patients, will also be tracked. Recommendations/Conclusions Preliminary pilot shows that integrating a standardized visual education tool into routine ENT preoperative workflows is feasible and acceptable. Future testing could expand and adapt the tool across multiple pediatric surgical service lines and languages to improve patient safety and caregiver experience. Ongoing feedback can help refine its content and delivery, demonstrating that low-cost educational innovations effectively address health literacy gaps.
-

Fierce and Focused - Virtual Reality Support for Pediatric Oncology Patients
Javarius Barber-Esparza
Practice Problem: Pediatric oncology patients often experience anxiety during needle procedures. Even with anesthetic pain management in place, visually encountering the needle can be more distressing than the procedure itself. Virtual Reality (VR) has emerged as a nonpharmacological tool that provides immersive distraction, effectively lowering pain perception and anxiety. Studies show VR reduces anxiety during medical procedures, including accessing Implanted venous access devices (IVAD). Yet, its adoption in pediatric oncology settings remains limited.
Literature/Evidence: Search strategy in the CINAHL (EBSCOhost) database used MeSH headings and keywords, including English articles published within the last five years. Studies show that VR reduces pain, anxiety, and fear during procedures. A 2024 meta-analysis found VR led to 50% lower pain scores and improved physiological responses. Most children (85.7%) expressed willingness to reuse VR. Customizable programs enhance engagement and support patient-centered care. Integrating VR at the bedside addresses a gap in coping tools, aligning with ethical responsibilities to reduce trauma and improve procedural experiences.
Practice Change: This project integrates virtual reality (VR) as a standard distraction during IVAD access for pediatric oncology patients. This initiative engages pediatric hematology/oncology nurses in implementing VR to reduce procedural distress. Nurses, positioned at the intersection of technical and emotional care, play a central role in delivering this evidence-based, immersive intervention. This shift supports patient-centered care, enhances pain management, and promotes emotional safety without disrupting clinical workflow.
Implementation: A team of trained VR champions, nurses, patient care technicians, and child life specialists, will support implementation under the project lead guidance. Champions will receive 1:1 training on setup, maintenance, and patient coaching. VR will be integrated into IVAD access workflows, with age-appropriate apps selected to boost engagement. The project begins with an inpatient pilot, expanding to outpatient use. Staff engagement will be supported through debriefings, coaching, monthly updates, and standardized scripts to ensure consistent, effective implementation.
Outcomes/Results: Initial outcomes from the pilot demonstrated positive patient responses to VR use during IVAD access. One patient removed the headset prior to the procedure, expressing a desire to visually observe the process, highlighting the importance of patient autonomy and individual coping styles. Another patient, who had no prior VR experience, reported that the procedure felt better with VR and expressed willingness to use it again. Early observations suggest that VR can enhance procedural tolerance and support varied patient preferences, reinforcing its value as a customizable, patient-centered intervention.
Recommendation/Conclusion: Early results support the feasibility and acceptability of VR as a nonpharmacological strategy for reducing distress during IVAD access in pediatric oncology patients. The intervention will be expanded to additional pediatric units, with long-term sustainability supported by integrating VR into routine workflows and providing ongoing training and refresher sessions for staff. Future phases of this initiative will explore the use of augmented reality (AR) glasses for patients who prefer to remain partially engaged with their environment rather than fully immersed. This next step aims to broaden accessibility and accommodate a wider range of patient coping preferences, further advancing emotionally supportive, patient-centered procedural care. -

Increasing Clinical Internal Mobility Through a Student Nurse Technician Program
Radiance G. Bean
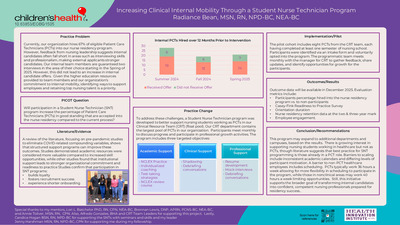
Practice Problem: Currently 67% of internal applicants are hired into our nurse residency program. Feedback from nursing leadership suggests internal candidates often fall short in areas like interviewing skills and professionalism, making external candidates stronger. Given the higher education resources provided to team members and our organization’s commitment to internal mobility, identifying ways to support employees and retaining top nursing talent is a priority. Our EBP question is: Will participation in a Student Nurse Technician (SNT) program increase the percentage of Patient Care Technicians (PCTs) in good standing that are accepted into the nurse residency compared to the current process.
Literature/Evidence: Using CINAHL Ultimate, search criteria included key word search terms: nurse apprenticeships, nurse assistant roles, recruitment and retention of Unlicensed Assistive Personnel. A review of the literature, focusing on pre-pandemic studies to eliminate COVID-related compounding variables, shows that structured support programs can improve outcomes. Studies confirm that participation in SNT programs builds loyalty and fosters recruitment success. According to Haqq-Stevens et al. (2017), academic resources were considered more valuable compared to increased skill opportunities. While Lokmic-Tomkins et al. (2021) found that institutional support leads to stronger organizational commitment and readiness to practice.
Practice Changes: To address these challenges, a Student Nurse Technician program was developed to better support nursing students working as PCTs in our Clinical Resource Team (CRT) (float pool). Participants meet monthly to discuss progress and participate in professional growth activities. The program includes three targeted components:
Academic Support: Offers NCLEX practice tests, individualized coaching, and test-taking strategy sessions, culminating in an NCLEX review course during their final semester.
Clinical Support: Provides exposure to various hospital units through shadowing, followed by debriefing conversations to help participants assess their preferences for nurse residency placement.
Professional Support: Provides feedback with resume development, mock interviews, and one-on-one interview debriefs to enhance their interview skills.
Implementation/Pilot Testing: The pilot cohort includes eight PCTs from the CRT, each having completed at least one semester of nursing school. Participants were identified via an intake form and voluntarily opted into the program. Leaders were provided with a schedule to ensure appropriate staffing and enhance flexibility.
Outcomes/Results: Outcome data will be available in December 2025. Evaluation metrics include the percentage of participants hired into the nurse residency program compared to non-participants, Casey-Fink Readiness to Practice Survey results (pre-program, in the program, and program end), and orientation duration. Literature indicates that participants in support programs typically experience shorter onboarding periods (Flint, 2023), which will be another indicator of program success.
Recommendations/Conclusions: Based on the results, the program may expand to include additional departments and campuses. There is growing interest in supporting nursing students who work in healthcare but not as PCTs, though literature suggests that best practice for SNT programming is those already in a PCT role. Barriers to scaling include inconsistent academic calendars and differing levels of participant motivation. Still, this initiative supports the broader goal of transforming internal candidates into confident, competent nursing professionals prepared for residency success. -

Elevating Nursing Leadership: How Nurse Managers Empower Unit Practice Councils
Katie Fields
Problem: Unit Practice Councils (UPCs) are foundational to Nursing Professional Governance (NPG), a structure that is designed to foster autonomy, accountability and authority for nurses. These councils are vital for empowering nurses to engage in decision-making and implementing practice changes. At one large pediatric hospital, UPC effectiveness varied across units, largely due to differences in nurse manager engagement and support. This variation highlighted a critical gap in how nurse managers were supporting UPCs within their unit. To close this gap, it was important to identify leadership best practices and behaviors that lead to successful UPCs. The following PICOT question was developed: “What are the best practices and leadership behaviors of nurse managers to support Nursing Professional Governance Unit Practice Councils?”
Literature/Evidence: Utilizing OVID and databases, CINAHL and PubMed, a comprehensive review of 22 articles, including integrative reviews and qualitative studies, was conducted to explore leadership behaviors that support NPG and UPCs. Across literature, empowerment, accountability, and presence are frequently highlighted as essential leadership behaviors for effective shared governance that enhances engagement and growth. Clavelle and Tarasenko (2024) emphasized accountability as key to advancing NPG, while Rollins et al. (2024) stressed the importance of adaptable leadership styles.
Practice Change: To address the variation in UPC effectiveness across units, a practice change initiative was implemented to examine whether the leadership behaviors demonstrated in high-performing UPCs aligned with those identified in the literature. The evidence highlighted key behaviors such as effective communication and collaboration, relational leadership practices, leadership support, empowerment and shared decision-making. To explore this alignment, a questionnaire was developed consisting of open-ended questions aimed at uncovering recurring themes in leadership behaviors that contribute to the success and sustainability of UPCs within the organization.
Implementation: Using the developed questionnaire, structured interviews were conducted with UPC leaders and nurse managers from four high-performing units to explore alignment between leadership behaviors demonstrated in practice and those identified in the literature. The qualitative data collected was thematically coded and analyzed across roles to identify the recurring themes.
Outcomes: Following the interviews, a consensus emerged regarding the leadership behaviors that contributed to the individual success of the UPCs. Relational leadership, consistent support and shared decision-making emerged as key drivers of UPC effectiveness, aligning closely with evidence from literature. UPC leaders consistently expressed that feeling supported and empowered by their nurse manager was crucial for their ability to lead. These best practices were integrated into annual NPG training to elevate and standardize UPC performance.
Recommendations: The findings from this initiative underscored the critical role of leadership behaviors in the success and sustainability of UPCs. It is recommended to integrate these best practices into leadership development programs and ongoing NPG training. Nurse managers should be equipped with tools and strategies to cultivate relational leadership, provide visible and meaningful support, and facilitate collaborative decision-making. By standardizing these leadership behaviors, organizations can strengthen the foundation of NPG, enhance nurse engagement, and improve patient outcomes. Continued evaluation and feedback from UPC leaders will be essential to refine these practices and ensure their sustained impact across the organization.
-

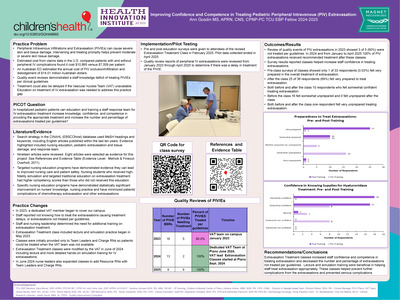
Improving Confidence and Competence in Treating Pediatric Peripheral Intravenous Extravasation
Ann Gosdin
Practice Problem: Peripheral Intravenous Infiltrations and Extravasation (PIVIE) can cause severe skin and tissue damage. Prompt intervention helps prevent moderate or severe skin tissue damage. In the U.S. PIVIE complications can cost $10,895 versus $7,009 per patient without PIVIE. An Australian ED estimated the annual cost of PIV occlusion/infiltration and dislodgement of $14.01 million Australian dollars.
Quality event reviews demonstrated a staff knowledge deficit of treating extravasations per guidelines. Treatment could be delayed if the Vascular Access Team (VAT) was not available. Education on treatment of IV extravasation was needed to address this practice gap.
PICO(T) Question: In hospitalized pediatric patients can education and training a staff response team for IV extravasation treatment increase knowledge, confidence, and competence in providing the appropriate treatment and increase the percentage of extravasations treated per guidelines?
Literature/Evidence: Search strategy in the CINAHL (EBSCOhost) database used MeSH headings and keywords, including English articles published within the last ten years. Evidence highlighted included nursing education, pediatric extravasation and tissue damage, and response team.
Targeted nursing education programs have demonstrated they can improve nursing care and patient safety. Nursing students who received high-fidelity simulation and targeted traditional education on extravasation treatment had higher competency scores than those who did not received this education.
Specific nursing education programs have demonstrated statistically significant improvement on nurses' knowledge, practice and minimized patients' complications of chemotherapy extravasation.
Practice Change(s): In 2023, a dedicated VAT member began staffing our campus. Staff reported not knowing how to treat extravasations, causing treatment delays, or extravasations not being treated per guidelines. Staff and nursing leadership determined the need for additional training on extravasation treatment.
Extravasation Treatment classes including lecture and skills practice began in May 2023. Classes were provided only to Team Leaders and Charge RNs so patients could be treated when the VAT team was not available. Classes were modified by VAT in June 2024 including lecture and hands skills training for PIVIEs. In June 2024 nurse leaders expanded classes to add Resource RNs with Team Leaders and Charge RNs.
Implementation/Pilot Testing: Pre / post education surveys were given to attendees of the revised Extravasation Treatment Class in February 2025. Pilot data collection ended in May 2025.
Quality review reports of PIVIEs were reviewed from January 2023 through April 2025 to determine if there was delayed treatment or PIVIE not treated per guidelines.
Outcomes/Results: Quality reports of PIVIEs in 2023 showed 3 of 5 (60%) were not treated per guidelines. In 2024 and from January to April 2025 100% of PIVIEs received recommended treatment after these classes.
Surveys showed classes increased staff confidence in treating extravasations. In pre-class surveys classes only 1 of 33 respondents (0.03%) felt very prepared in overall treatment of extravasation. After classes 25 of 36 respondents (69%) felt very prepared to treat extravasation.
Recommendations/Conclusions: Lecture and skills training were beneficial in helping staff treat PIVIE per guidelines. Extravasation Treatment classes increased staff confidence and competence in treating extravasation and decreased the number and percentage of PIVIEs not treated per guidelines. -

Ask Me 3® in Action Advancing Health Literacy in Pediatric Acute Care
Yaseming Medina
Background: Parents and caregivers’ understanding of how to provide safe and effective care at home is vital. However, elevated levels of stress and limited health literacy face significant challenges in understanding discharge instructions.
For parents of pediatric patients seen in an acute perioperative setting, how will the use of the Ask Me 3® health literacy tool impact understanding of medical information and communication with healthcare providers?
Literature Evidence: Patients who understand heath instructions make fewer mistakes when they take their medicine, follow treatment plans, and prepare for medical appointments (Six-Means, Amy, et al, May 2012). Patients have reported higher satisfaction and found that the use of Ask Me 3® was helpful in learning more about their medical condition (Vaillancourt & Cameron, May 2021).
Practice Changes: Multidisciplinary team lead initiative, including Unit coordinator, patient care techs, and unit nurses. Unit printed The Ask Me 3® handout in both Spanish and English and provided to caregivers during the preoperative phase. Postoperative nurses reviewed discharge instructions and Project leader assessed if the Ask Me 3® tool was reviewed with them, if they found it useful, and if they felt confident in caring for their child at home.
Implementation: The Ask Me 3® handout was introduced by nursing staff during the preoperative phase using a standardized script. Caregivers of pediatric patients were asked after preoperative check in was completed and postoperatively if the tool had been reviewed. If not reviewed, it was introduced at that time. Discharge instructions were reviewed during the post-operative phase and included Did I explain things in a way you can understand? This question is a National Research Corporation (NRC) Health® Nurse Sensitive indicator. The introduction of the Ask Me 3® tool was tracked, and NRC scores were compared across quarters using the NRC Health benchmarks from 2025 Quarter1 (2025Q1) as baseline and 2025 Quarter2 (2025Q2) post-intervention.
Results: The intervention led to marked improvements and outperformed the benchmarks set by the NRC Health® in Care Coordination, Careful listening, Patient Education, Responsiveness Communication, and Service Recovery. Caregivers who felt that communication between the different doctors and nurses improved from hospital score of 25.0 in 2025Q1 to 100.0 in 2025Q2. Similarly, caregivers reported that discharge instructions clear and surpassed the set benchmark and 2025Q1 hospital score of 50.0 to 100.0 in 2025Q2. Comfort in talking to nurses about their worries or concerns as well as their perception of the nurse listening carefully to them also outperformed the 2025Q1 hospital scores and set benchmarks from 50.0 to 100.0, respectively.
Conclusions: Ask Me 3® tool was effective in improving communication, clarity, and caregiver confidence in understanding postoperative discharge instructions. Challenges in implementation including caregivers’ recollection about the introduction of the Ask Me 3® tool when interviewed, information overload, and or child distress during interviews. Recommendations include revaluating the format and delivery of written materials to reduce redundancy, improve clarity, and caregiver engagement. Next steps include fostering team involvement, ongoing evaluation of the Ask Me 3® tool and how written materials presented to caregivers ensure long-term sustainability and adoption. -

Empowering Nurses: A Training Initiative on Essential Oils for Pediatric Neurosurgery Patients
Sheri Sacks
PICO Question: In pediatric neurosurgical bedside nurses, does education on lavender essential oil, compared to no education, improve knowledge, confidence and intent to integrateit as a complementary therapy for TBI patients?
Literature Review: Pediatric neurosurgery patients often face increased anxiety and agitation. Nurses may lack knowledge of non-pharmacological interventions to reduce agitation and anxiety in their patients. Literature review used MeSH Headings and keywords to find recent English articles. Evidence shows EO reduces anxiety. Lavender inhalation lowers anxiety, pain, and vital signs in pediatric dental patients. In adults, aromatherapy decreases anxiety, pain, blood pressure, and improves sleep, also reducing pain and extubation time.
Evaluation: Nurses' knowledge of EO benefits was evaluated, and education was provided in staff meetings. Twenty-two nurses completed the pre-questionnaire and twenty-seven the post-questionnaire. In the pretest, 73% of nurses had experience using EO, compared to 59% in the posttest. EO use was mainly seasonal. Most nurses(86%) had never received EO education in the pretest, compared to 59% in the posttest. In the pretest, 87% rated their understanding of EO as slightly or not at all knowledgeable, decreasing to 71% in the posttest. Only 59% were likely or very likely to consider lavender EO for pain, agitation, or anxiety in neurosurgery patients in the pretest, compared to 92% in the posttest. Before education, 59%believed neurosurgery patients could benefit from EO, increasing to 85% after. All felt they gained some or comprehensive knowledge, and 92% wanted more EO education. EO education boosted nurses' knowledge and willingness to use EO with pediatric neurosurgery patients.
Children's Health is proud to present the posters of our EBP Fellows. Many of our nursing EBP Fellows graduate from Texas Christian University, but other universities are also attended by our graduates.
You can view them as a Collection here, or by year through our Exhibits.
Printing is not supported at the primary Gallery Thumbnail page. Please first navigate to a specific Image before printing.